


A patient who is in pain, cannot sleep or lies in an uncomfortable bed cannot recover well, however good the medicines are. Comfort, rest, sleep and pain relief are basic needs, and a nurse is the person who looks after them every hour of the day. In this chapter you will learn about the types of comfort and comfort devices, bed making, therapeutic positions, the physiology and disorders of sleep, and the physiology, assessment and management of pain.
Learning Objectives
After reading this chapter, you will be able to:
- Describe comfort and the factors influencing comfort.
- Name the various comfort devices and explain their use in the hospital.
- Describe the principles of bed making and the types of beds.
- Explain therapeutic positions and their uses.
- Describe the physiology of sleep, the factors affecting rest and sleep, common sleep disorders and the nursing strategies to promote sleep.
- Define pain, its types and physiology; describe the factors influencing pain; perform a pain assessment.
- Describe pharmacological and non-pharmacological pain relief and the nursing management of pain.
Chapter Outline
- Comfort and factors influencing comfort
- Comfort devices and their use
- Bed making: types and procedure
- Therapeutic positions
- Rest and sleep: assessment, alteration and management
- Pain: types and management
1. Comfort
The word comfort comes from the Latin word ‘comfortare’, which means ‘strengthen greatly’. To give comfort means to strengthen a person’s physical state or to cheer up the person’s mood.
Definition: Comfort is the absence of irritating stimuli that divert one’s attention from the work to be done.
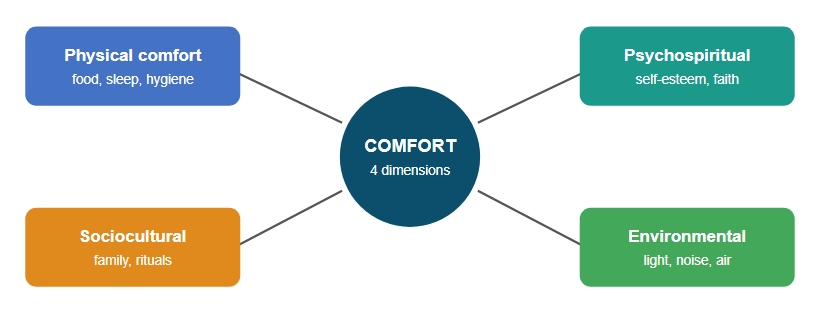
1.1 Types / Factors Influencing Comfort
COMFORT 4 dimensions Physical comfort food, sleep, hygiene Psychospiritual self-esteem, faith Sociocultural family, rituals Environmental light, noise, air Fig. 1: Dimensions of comfort
| Type | What it includes |
|---|---|
| Physical comfort | Eating and drinking, elimination of waste, mobility, personal care (bathing, brushing teeth, combing hair, clean clothes), recreation and sound sleep of at least 6–8 hours. |
| Psychospiritual comfort | Self-esteem, identity, sexuality, relationships, safety, faith and spirituality. |
| Sociocultural comfort | Family, society and interpersonal relationships; traditions, rituals and religious practices. |
| Environmental comfort | Accommodation, room colour, light, sound, odour, temperature, fresh air, etc. |
2. Comfort Devices
In hospital, many mechanical devices are used for the comfort of the patient. A nurse must know the use of each device, quickly assess the patient’s individual need, and use the device correctly to get the therapeutic result.
Purposes of Comfort Devices
- To relieve discomfort of the patient.
- To immobilise a body part when required.
- To give a comfortable position.
- To relieve pressure on body parts so that decubitus ulcers (bed sores) are prevented.
- To prevent patient falls and accidents.

2.1 Special Beds
| Bed | Key points |
|---|---|
| Gatch bed | Frame in three movable sections with mechanical spring parts. The head end, foot end or middle part can be raised as needed. |
| Electric bed | Same functions as Gatch bed but operated electrically. Advantage: the patient can also operate it. |
| Clinitron bed | For therapeutic treatment of patients with advanced or multiple pressure ulcers, burns, grafts and intractable pain. It supports the body weight evenly. |
2.2 Other Comfort Devices
| Device | Description and use |
|---|---|
| Pillows | Most commonly used. Support body parts (head, arms, legs, back, abdomen) to maintain body alignment and reduce pressure, so bed sores are prevented. |
| Mattresses | Must fit the bed frame. Types: standard bed mattress, egg-crate mattress, air mattress, water mattress. |
| Back rest | Supports the back at an angle so that the patient can keep a sitting or Fowler’s position. |
| Cardiac table | Also called orthopneic table / bed table. An over-bed table placed in front of the patient in Fowler’s position. |
| Bed cradle | Wooden or metal frame, semicircular or rectangular. It keeps the weight of bed clothes off the patient’s body (useful in burns and painful limbs). |
| Air cushion | Round, made of rubber. Prevents direct pressure on bony prominences and improves blood circulation (e.g., lifting the hip off the bed). |
| Cotton rings | Cotton wrapped with bandage. Placed under bony areas such as heels to relieve pressure. Plastic rings can also be used. |
| Trochanter roll | Prevents external rotation of the hip in supine position. Made by folding a cotton bath blanket/sheet lengthwise and placing it from the greater trochanter of the femur to the lower border of the popliteal space. |
| Hand roll | Cloth rolled into a cylinder, about 2–3 inches in diameter and 4–5 inches long. Placed against the palm to keep the fingers slightly flexed and prevent a tight fist. |
| Sandbags | Canvas, rubber or plastic bags filled with sand. Immobilise body parts, give support and shape to body contours and maintain alignment. |
| Hot water bag | For hot application: reduces inflammation, relieves pain, promotes healing and gives warmth. Always cover with cloth – direct contact can burn the skin. |
| Ice pack | Plastic pack with ice cubes for cryotherapy. Relieves pain of sprains, strains and soft tissue injuries and reduces inflammation by reducing blood flow to the area. |
| Side rails | Bars along the sides of the bed. Ensure safety and help the patient to roll or sit up. |
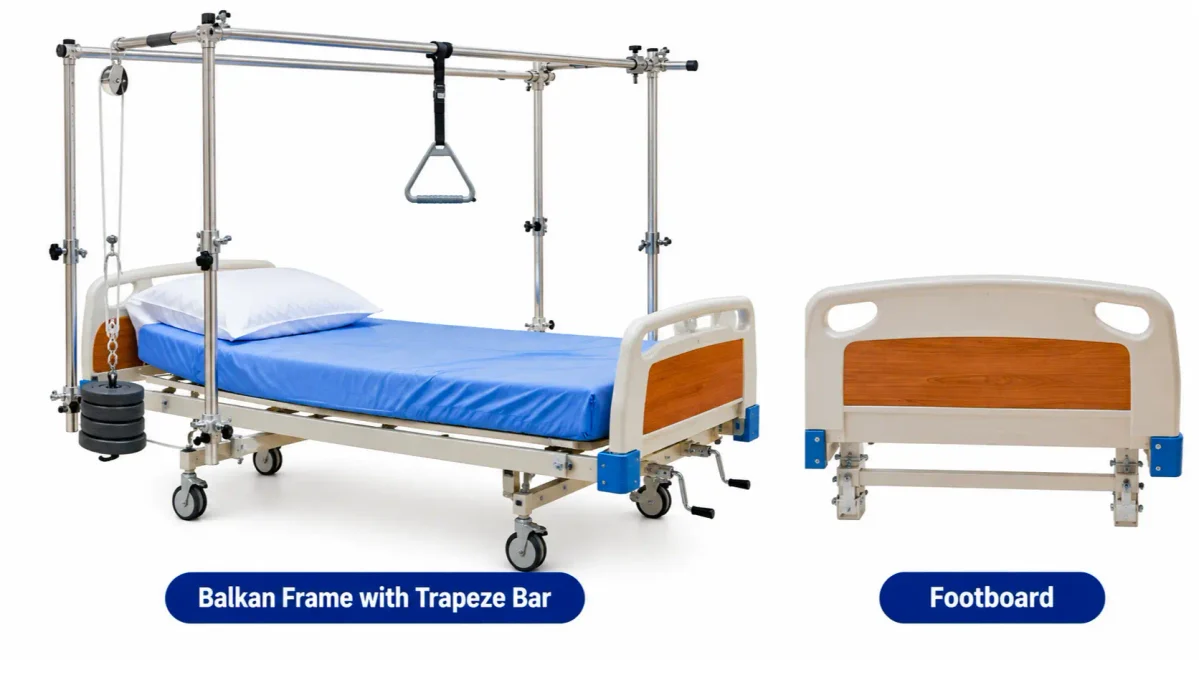
| Footboard | Supports the feet and maintains their normal position to prevent foot drop in unconscious patients. Placed at the foot end of the bed. |
| Foot end elevator | Platform that is raised/lowered to give elevated support to feet and ankles. Ideal for postoperative and rehabilitation patients. |
| Wedge / abductor pillow | Triangular pillow of heavy foam. Keeps legs in abduction after total hip replacement surgery. |
| Knee rest | Placed under the knees for comfort; relaxes and relieves pain on tendons beneath the knee. |
| Bed blocks | Wooden or metal blocks that raise the foot end or head end of the bed. Used for Trendelenburg and reverse Trendelenburg positions. |
| Trapeze bar | Hangs from an overhead frame. Patient holds it to lift the trunk or move up in bed. Also a safety device. |
| Balkan frame | Wooden/metal frame running lengthwise above the bed, supported by poles at both ends. A trapeze can be attached to it above the patient’s head. |
| Hand and wrist splints | Individually moulded; keep the thumb in slight adduction and wrist in slight dorsiflexion. Use only for the patient for whom it was made. |
3. Bed Making
Definition: Bed making is the act of arranging bed sheets and other bedding on a bed to prepare it for therapeutic use. It is a basic nursing procedure to prepare different types of beds so that the patient is placed in a comfortable position suitable for his/her condition.
3.1 Purposes of Bed Making
- To promote cleanliness of the patient.
- To provide a safe and comfortable bed for rest and sleep.
- To observe, identify and prevent complications such as decubitus ulcers.
- To establish an effective nurse–patient relationship.
- To give physical and psychological comfort and security.
- To provide active and passive exercise.
- To give the unit/ward a neat appearance.
3.2 Principles of Bed Making
- Principle of patient comfort
- Principle of body mechanics
- Principle of order
- Principle of prevention of spread of micro-organisms
- Principle of patient safety
- Principle of assessment
3.3 Body Mechanics During Bed Making
| Body mechanics | What the nurse should do |
|---|---|
| Stability | Keep the centre of gravity over the base. Keep the feet apart to make a wide base. |
| Body weight | Keep weight close to the centre of gravity. Place linen on the edge of the bed when opening it, rather than holding it above shoulder level. |
| Bed height | Raise the bed to a suitable height before changing linen so that you do not have to bend or stretch over the mattress. |
| Safe handling | Use body mechanics and safe handling when turning or repositioning the patient. |
| Body positioning | While tucking sheets, flex knees and hips. This shifts the work to the strong thigh muscles and keeps the back straight. |
| Direction | Face the direction of work and move with the work. Do not twist the body or over-reach. |
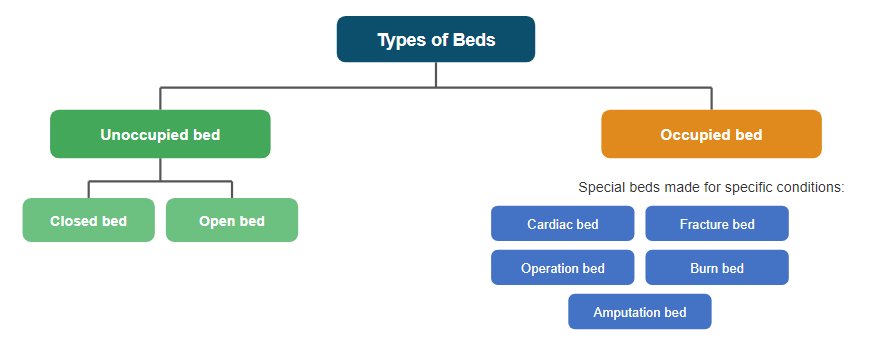
3.4 Types of Beds
3.5 Articles Required for Bed Making
- Mattress cover; two sheets (bottom and top sheet); blanket; draw sheet; mackintosh; pillow cover; counterpane
- Laundry bag; two dusters / sponge cloths (one for solution, second to dry)
- A bowl with antiseptic lotion (Savlon or Dettol solution); kidney tray
- Comfort devices as needed: cardiac table, bed cradle, extra pillows, back rest, footboard, fracture board, sandbag, etc.

3.6 Details of Each Bed
| Bed | Meaning | Purposes |
|---|---|---|
| Unoccupied bed | A bed prepared to receive a new patient. Two types: closed bed and open bed. | Suitable bed ready for admission; clean and fresh environment; reduce source of infection; promote cleanliness; neat appearance of ward. |
| Occupied bed | Made with the patient in the bed who cannot get out of bed. Commonly used for immobile patients. | Make the bed with least discomfort to the patient; prevent skin breakdown due to soiled linen; handle linen skilfully while patient is on bed; clean and tidy appearance; build nurse–patient relationship. |
| Postoperative bed (operation / surgical bed) | Special bed for a patient coming from the operation theatre or another procedure. Made so that an unconscious or weak patient can be easily shifted from the stretcher to the bed. | Receive the patient conveniently; prevent shock; meet any emergency; provide warmth and comfort. |
| Cardiac bed | Prepared for patients with cardiovascular and respiratory diseases. | Relieve dyspnoea; maintain comfort of cardiac/respiratory patients. |
| Amputation bed | Bed in which the top linen is divided into two parts so that the amputated lower limb can be seen without disturbing the patient. | Watch the stump for haemorrhage; take the weight of the bed clothes; keep the stump in position. |
| Fracture bed | For patients with fracture, bone diseases and deformity. | Immobilise the fractured part; restrict sudden jerky movements; prevent sagging of the mattress; keep traction in position. |
| Burn bed | Special bed for patients with severe skin burns over a large part of the body. | Provide comfort; relieve pain; prevent infection; distribute the weight of the top sheet equally over the cradle. |
Exam tip: Remember the uses in one line – Cardiac = breathing, Amputation = bleeding (stump), Fracture = traction, Burn = cradle, Operation = shock.
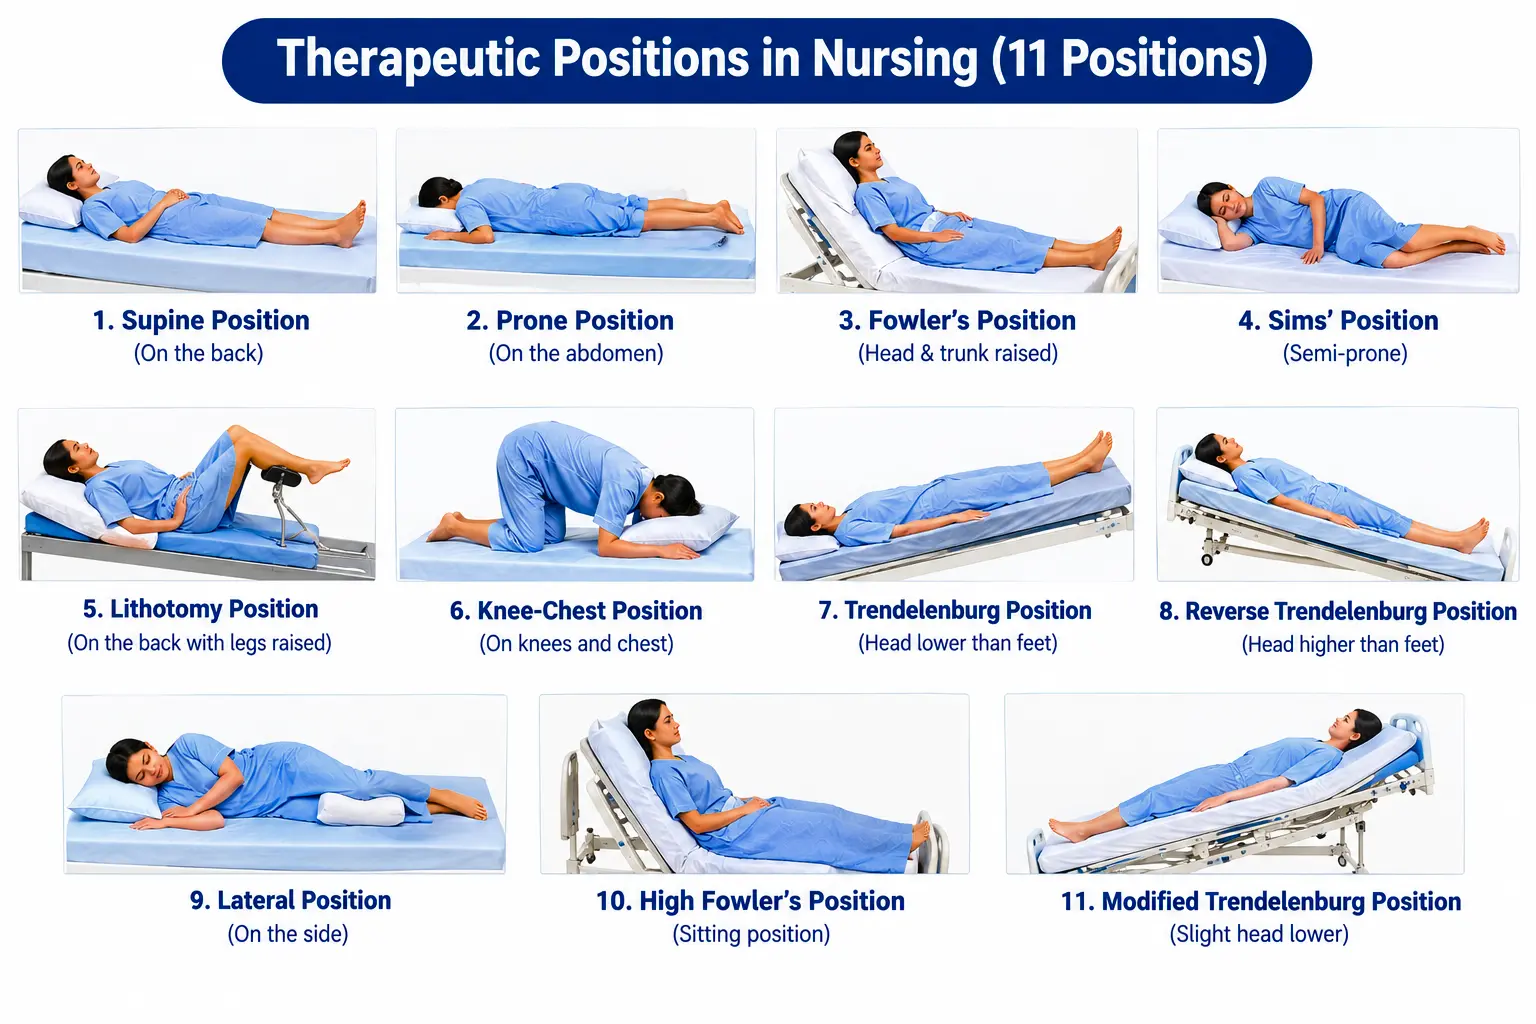
4. Therapeutic Positions
Positioning is placing the person in correct body alignment for promotive, preventive, curative and rehabilitative purposes, or placing the patient in proper body alignment as needed therapeutically.
Body alignment means the condition of the joints, tendons, ligaments and muscles in different body positions – standing, sitting or lying.
4.1 Principles of Positioning
- Follow safety measures to prevent accidents.
- Maintain good body alignment of yourself and the patient.
- Maintain good body mechanics.
- Change the position regularly (every 2 hours) and systematically.
- Inspect pressure points during each position change.
4.2 Purposes of Positioning
- Permits frequent skin assessment and maintains skin integrity.
- Ensures comfort and enhances sleep.
- Prepares patients for diagnostic procedures and treatments.
- Facilitates recovery and prevents contractures.
- Prevents decubitus ulcers and other complications of immobility.
- Good positioning stimulates the nervous system.
4.3 Guidelines for Positioning Patients in Bed
- Use supportive devices according to the individual’s body and ability (an emaciated patient needs lumbar support; a muscular patient with enough fat may not).
- Change the position of a helpless patient every 2 hours to improve circulation and prevent skin breakdown.
- Give skin care to pressure areas created in the previous position.
- Make sure the bed foundation is firm and clean and the mattress is dry.
- Unless contraindicated, give range of motion exercises to major joints at each position change.
4.4 List of Therapeutic Positions
Supine, Prone, Fowler’s, Cardiac/Orthopneic (Tripod), Dorsal recumbent, Lateral (side-lying), Sims’ (lateral decubitus), Trendelenburg, Reverse Trendelenburg, Lithotomy and Knee-chest (Genu-pectoral).
| Position | Description | Uses |
|---|---|---|
| Supine (horizontal recumbent) | Lying on the back with arms at the sides and legs straight; head on a pillow, neck neutral. | General rest; basic position for many procedures. |
| Prone | Lying on the abdomen with head turned to one side. Pillow under head, one under waist and one under ankles (to free the toes from weight). Arms above head or alongside the body. | The only bed position that allows full extension of hip and knee joints. |
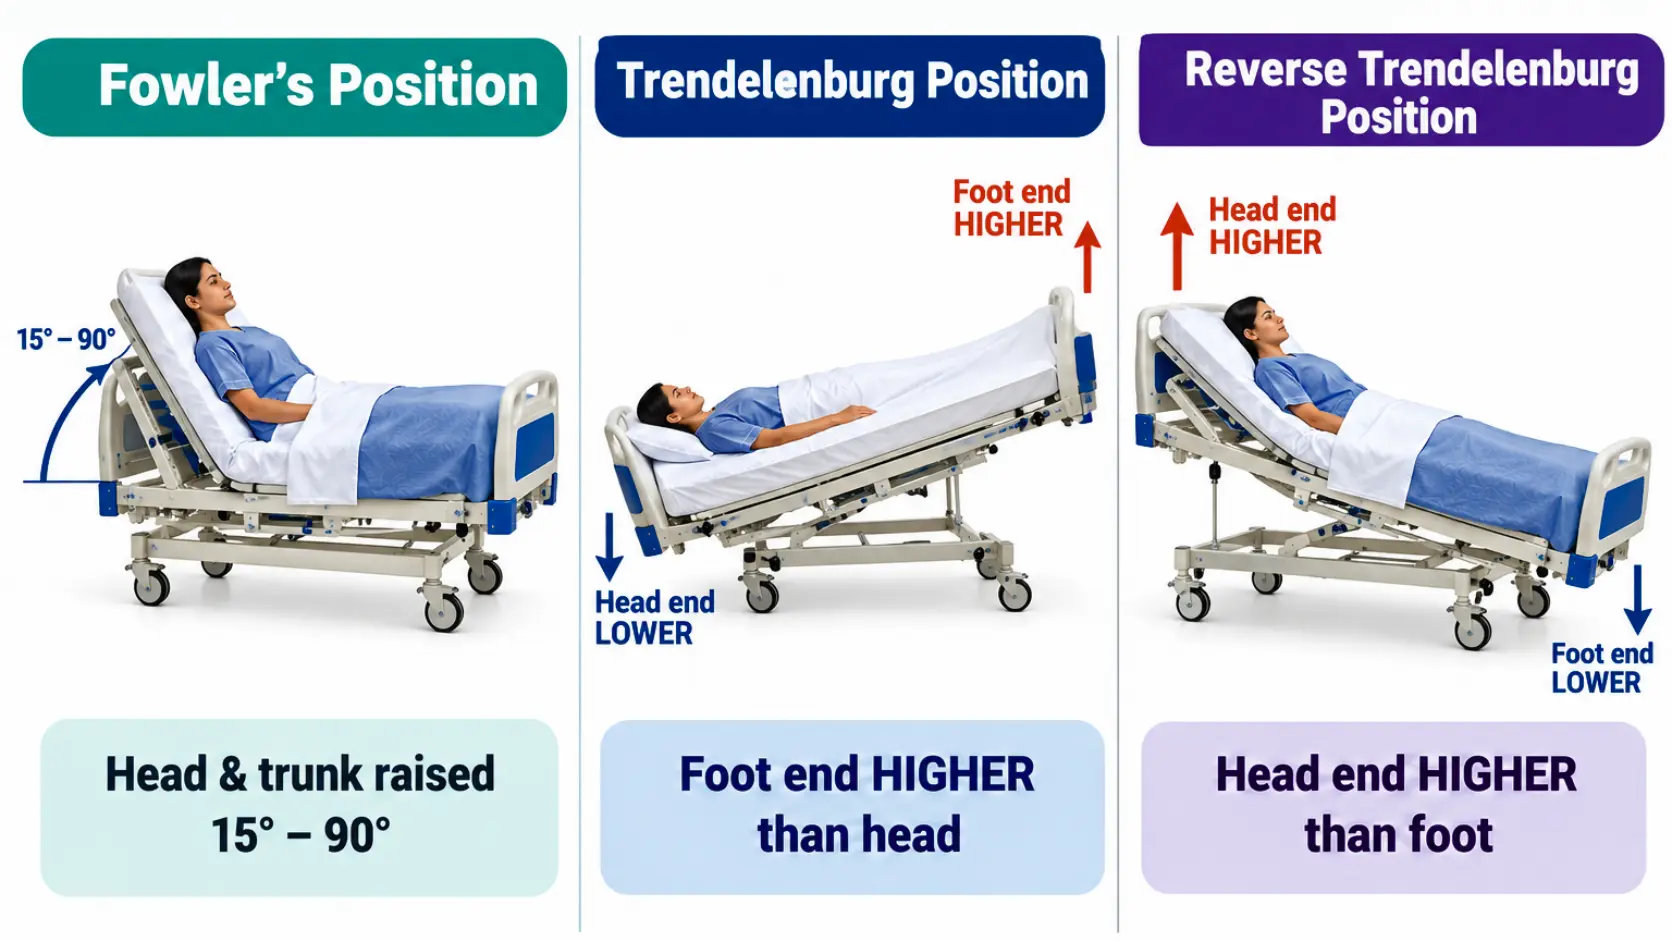
| Fowler’s | Semi-sitting position; head and trunk raised 15°–90°. Knees may be bent or straight; small pillow or rolled towel under knees to prevent pressure at the back of the legs. Given with backrest and pillows. | Breathing difficulty, feeding, comfort. |
| Cardiac / Orthopneic / Tripod | Sitting upright with the head of bed elevated 90°; patient may lean slightly forward with arms raised and elbows flexed (usually on a cardiac table). | Easy breathing. Gives maximum lung expansion because abdominal organs do not press on the diaphragm. |
| Dorsal recumbent | Lying on the back, legs apart, knees bent, soles flat on bed, head and shoulders slightly raised on a small pillow. | Examination of abdomen and genitalia; perineal care, urinary catheterisation, vaginal douche, vulval, vaginal and rectal examination. |
| Lateral / side-lying | Lying on the right or left side. Pillows behind the back and between knees and ankles. Both knees slightly bent, upper knee bent more than the lower. | Relieves pressure on sacrum, coccyx and heels in patients who sit for long or are on bed rest in Fowler’s or dorsal position. |
| Sims’ (lateral decubitus) | Semi-prone position, halfway between lateral and prone. Lying on the left side; lower arm behind the body, upper arm flexed at shoulder and elbow; both legs flexed in front, right leg drawn up toward the chest. | Rectal examination or treatments of the rectal area. |
| Trendelenburg | Lying on the back, foot end higher than the head end, about 30° below horizontal. Use a pillow to protect the head from the headboard. | Standard position in abdominal and gynaecological surgery. |
| Reverse Trendelenburg | Opposite of Trendelenburg. Lying on the back, head higher than foot, no flexion at the waist. | Position of choice in gastrointestinal problems to minimise oesophageal reflux. |
| Lithotomy | Lying on the back with knees flexed above the hips and legs supported in stirrups. Similar to dorsal recumbent, but legs are well separated and thighs acutely flexed. | Examination and diagnostic procedures of pelvic organs; vaginal/gynaecological examination; surgeries like hysterectomy. |
| Knee-chest (genu-pectoral) | Patient kneels on the bed with thighs vertical and chest resting on a firm pillow; head turned to one side, hands flexed around the head or on bed; lower legs flat on bed. | Rectal and vaginal examination; treatment to bring the uterus into normal position. |
5. Rest and Sleep
Rest and sleep are essential for life and good health. The body needs both, and rest is an important part of restful sleep. Lack of rest or sleep harms a person’s physical, mental and emotional health.
Rest: A state in which the body is in reduced activity, giving a feeling of being refreshed.
Sleep (Buysse, 2014): A complex rhythmic state involving a progression of repeated cycles, each representing different phases of body and brain activity. It is crucial for physical, mental and emotional well-being.
Sleep health (Buysse, 2014): A multidimensional pattern of sleep–wakefulness, adapted to individual, social and environmental demands, that promotes physical and mental well-being.Sleep health (Buysse, 2014): A multidimensional pattern of sleep–wakefulness, adapted to individual, social and environmental demands, that promotes physical and mental well-being.
5.1 Stages of Sleep
Normal sleep has two stages: NREM (non-rapid eye movement) and REM (rapid eye movement). They are studied by polysomnography (sleep study), which combines three recordings:
- EEG (electroencephalograph) – electrical activity of the brain
- EOG (electro-oculogram) – eye movements
- EMG (electromyograph) – muscle tone
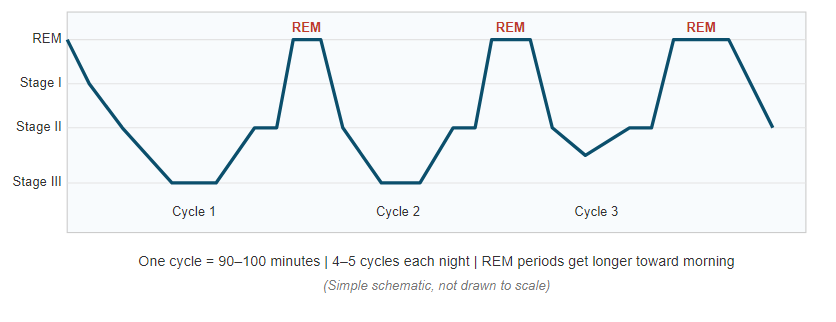
A hypnogram is a graph from the polysomnogram that shows the brain wave activity (EEG) across the night, the NREM and REM stages and any disruption of sleep.
5.2 NREM Sleep
NREM sleep makes up about 75% of total sleep time. According to the American Academy of Sleep Medicine (AASM), it has three stages. Stages I and II are light sleep; stage III is deep sleep.
| Stage | Duration / share | Features |
|---|---|---|
| Stage I – relaxed wakefulness | About 5 minutes; about 5% of total sleep | Transition from wakefulness to sleep. Person is relaxed but somewhat aware of surroundings. Slow eye movements; decreased muscle activity. |
| Stage II – light sleep | 10–25 minutes in each cycle; about 50–55% of total night sleep | First stage of true sleep. No eye movements; body temperature falls and heart rate begins to slow. |
| Stage III – deep sleep | About 20% of total sleep | Deepest sleep. Heart rate, BP, respiratory rate and body temperature decrease; muscles relax; metabolism slows. Arousal is difficult; if awakened, the person feels muzzy and disoriented for several minutes. |
5.3 REM Sleep
- Also called dream sleep. It starts about 70–90 minutes after falling asleep.
- About 20–25% of total night sleep in a normal adult.
- Features: rapid eye movements, muscle atonia, EEG desynchronisation.
- Heart rate and BP fluctuate, breathing becomes irregular, body temperature and metabolism begin to rise.
- Skeletal muscle tone and deep tendon reflexes are depressed (like paralysis).
- Arousal is harder than in NREM sleep; dreams occur often and are recalled vividly.
5.4 Sleep Cycle
- A person passes through the three NREM stages (I → II → III).
- Then the pattern reverses (III → II).
- Instead of going back to stage I, the person enters REM sleep, and then returns to NREM stage II and again to stage III.
- If a person is awakened at any time, sleep starts again from stage I of NREM.
- One cycle lasts about 90–100 minutes; a person has 4–5 cycles each night.
| Feature | NREM | REM |
|---|---|---|
| Share of sleep | About 75% | About 20–25% |
| Eye movements | None / slow | Rapid |
| Muscle tone | Relaxed, reduced | Atonia (paralysis-like) |
| Heart rate, BP, breathing | Decrease (deep stage lowest) | Fluctuate, irregular |
| Dreams | Few | Vivid and frequent |
| Arousal | Difficult only in stage III | Difficult |
5.5 Factors Affecting Rest and Sleep
- Age, motivation, culture, occupation
- Dietary habits, physical activity and exercise, lifestyle and habits
- Alcohol, caffeine, smoking
- Environmental factors (noise, light, temperature)
- Psychological stress
- Disease conditions and medications
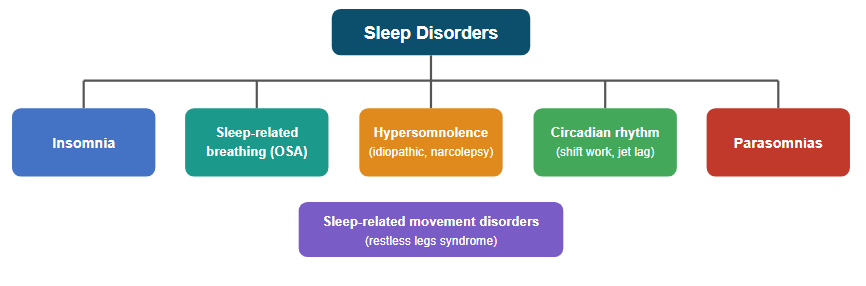
5.6 Sleep Disorders
A. Insomnia
Definition: Subjective perception of difficulty with sleep initiation, duration, consolidation or quality that occurs despite adequate opportunity for sleep and results in some form of daytime impairment (International Classification of Sleep Disorders, 2005).
- Acute insomnia: lasts from one week to a few weeks.
- Chronic insomnia: occurs at least 3 times per week and persists for at least 3 months.
Risk factors: age above 60 years, menopausal women, history of depression, disturbed circadian rhythm, periods of stress (shift work, pain, discomfort, limited mobility), and medication side effects (e.g., antihypertensives, cold/allergy medicines, ADHD and antidepressant drugs).
Daytime effects: feeling tired, lethargy, irritability.
Management:
| Non-pharmacological | Pharmacological |
|---|---|
| Sleep hygiene; Cognitive behavioural therapy (CBT) | Sedative-hypnotics; miscellaneous drugs |
Additional point – Sleep hygiene tips: go to bed and wake up at the same time daily; avoid caffeine, nicotine and alcohol in the evening; avoid heavy meals and screens before bed; keep the room dark, quiet and cool; exercise regularly but not just before bed; avoid long daytime naps.
B. Sleep-related Breathing Disorder – Obstructive Sleep Apnoea (OSA)
In OSA the throat muscles relax intermittently and block the airway during sleep, so breathing repeatedly stops and starts. It is of two types: adult OSA and paediatric OSA.
- Adult OSA: five or more mainly obstructive breathing episodes during sleep with fatigue, sleepiness, insomnia, snoring or observed apnoea/hypopnoea; linked with hypertension, atrial fibrillation, coronary artery disease, heart failure, diabetes, stroke, cognitive dysfunction or mood disorder (Sateia, 2014).
- Risk factors: increasing age, excess weight, large neck size, male sex, family history. Raises the risk of cardiovascular disease, depression, motor vehicle accidents and mortality.
- Manifestations: daytime irritability, poor concentration, falling asleep during monotonous activities, slow reaction time. Alcohol, tobacco and sleeping pills worsen it and should be avoided.
- Diagnosis: clinical information + polysomnography (overnight sleep study with video recording of sleep-awakening and body movements).
- Management:
- Mandibular advancement device (MAD): custom-made oral appliance for mild OSA, fitted by a dentist/orthodontist.
- CPAP (continuous positive airway pressure): definitive treatment of moderate and severe OSA; a snug mask connected to an air pump, worn during sleep.
- Surgery: removal of soft tissue at the back of the mouth if CPAP and MAD fail.
- Paediatric OSA: presence of snoring, laboured breathing, enuresis, or daytime effects such as hyperactivity, sleepiness, fatigue (Sateia, 2014).

C. Central Disorders of Hypersomnolence
Marked by excessive daytime sleepiness that is not caused by other sleep disorders such as breathing disorders or circadian rhythm problems.
| Disorder | Key points |
|---|---|
| Idiopathic hypersomnia | Excessive sleep, especially in the daytime. Person may fall asleep at work, while eating, driving or talking. When awake: irritable, disoriented, restless, slow speech, disturbed thinking. Occurs in adolescents and young adults. Not usually life-threatening but may cause road accidents. Treatment is symptomatic: stimulant drugs, sometimes antidepressants; quit alcohol, avoid caffeine, avoid night work and late-evening social activity. |
| Narcolepsy | Overwhelming daytime sleepiness and sudden, unintended lapses into sleep (even standing, talking, driving or swimming). About 70% have cataplexy – sudden loss of muscle tone from slurred speech to total body paralysis. Falls asleep quickly, finds it hard to wake, sleeps fewer hours and restlessly. Starts in adolescence or early adulthood, life-long, no cure at present. |
D. Circadian Rhythm Sleep–Wake Disorders
A chronic or recurrent pattern of sleep–wake disturbance caused by disruption of the internal body clock or a mismatch between it and the sleep–wake schedule, with distress, lasting at least 3 months (except jet lag). The most common are shift work disorder and jet lag disorder.
- Shift work disorder: working outside the usual 9 am–5 pm schedule against the body’s rhythm, causing difficulty sleeping or excessive sleepiness. Nurses are also affected by shift work.
- Jet lag disorder: temporary conflict between the body clock and the new time zone after travel across time zones. Symptoms: daytime fatigue, feeling unwell, poor alertness, gastrointestinal problems (Mayo Clinic, 2016).
Treatment:
- Behaviour therapy: regular sleep–wake timings, avoid naps, regular exercise, avoid caffeine, nicotine and stimulating activities before bedtime.
- Light therapy: exposure of the eyes to artificial bright light for a fixed period (the patient must be awake) – helps in jet lag.
- Chronotherapy: sleep time is delayed progressively by 1–3 hours until the desired schedule is reached.
E. Parasomnias
Patterns of abnormal waking-type behaviour during REM or NREM sleep. Common in children; safety and prevention of injury are the main concern. Treatment: regular sleep schedule, good sleep hygiene, adequate sleep; medication only if there is risk of injury or disturbance to others.
| Type | Description |
|---|---|
| Somnambulism | Sleepwalking – from sitting up in bed to walking around the house or outside. The person is unaware of the surroundings. |
| REM sleep behaviour disorder (RBD) | ‘Acting out’ dreams; the person may moan and thrash and may harm self or the bed partner. |
| Sleep terrors | Waking up screaming and sitting up in bed. Children seem awake but cannot communicate. |
| Nightmare disorder | Frightening, vivid dreams; more common in children and part of normal development. |
| Sleep enuresis | Bed-wetting; most common in males over 3 years of age. |
| Sleep-related eating disorder | Eating during sleep without remembering it. May occur with sleepwalking; can cause weight gain and injury (cooking or eating dangerous raw food). |
F. Sleep-related Movement Disorders – Restless Legs Syndrome (RLS)
- Also called Willis–Ekbom disease. Affects about 15% of the population, mostly middle-aged and older adults.
- The person cannot lie still and feels crawling, creeping or tingling sensations in the legs (usually calf, but anywhere from ankle to thigh), with an irresistible urge to move the legs, mostly in the evening and night.
- No specific diagnostic test and no known cure.
5.7 Sleep Deprivation
Sleep deprivation is a decrease in the amount, consistency or quality of sleep, often due to reduced REM or NREM sleep.
- Effects range from irritability and poor mental ability to total disintegration of personality. Effects become clear after about 30 hours of continuous wakefulness.
- Partial deprivation causes inattention, poor concentration and impaired information processing – serious safety risks.
- In hospital it occurs because of the strange environment, physical discomfort, pain, medicines and the need for 24-hour nursing care.
- Long-term deprivation can cause obesity, diabetes, cancer, delayed healing, cardiovascular disease and depression.
5.8 Nursing Process for Rest and Sleep
Assessment
| History collection | Physical assessment |
|---|---|
| Sleep–wake pattern, sleep duration, time of sleep Bedtime rituals, ideal sleeping environment Effect of sleep pattern on daily functioning Factors affecting sleep; use of sleep aids/medicines Presence of sleep disturbances and their causes Sleep diary | Reduced energy: fatigue, weakness, lethargy Face: glazed/narrow eyes, swollen eyelids, dry eyes Behaviour: rubbing eyes, slow speech, yawning, slumped posture Possible sleep problems: enlarged neck, obesity, deviated nasal septum Observation: restlessness, abnormal postures, snoring, leg jerking (RLS) |
Nursing Diagnoses (examples)
- Disturbed sleep pattern related to sleep apnoea, disturbed circadian rhythm, pain or discomfort, changed bedtime rituals or environment, hospital noise and periodic treatments.
- Risk for injury related to somnambulism, narcolepsy and sleep apnoea.
- Insomnia related to poor sleep hygiene, anxiety, worries about family and lack of bedtime rituals.
- Sleep deprivation related to frequent change of work shifts and overtime.
- Deficient knowledge related to lack of interest in learning, inadequate information and cognitive limitation.
Additional point – Common nursing interventions to promote sleep: reduce noise and light, keep a comfortable room temperature; give comfortable position and clean, dry linen; give a warm bath, back rub or relaxation techniques; follow the patient’s bedtime routine; avoid caffeine and heavy meals late in the evening; cluster nursing care so that the patient is not disturbed repeatedly; give prescribed sleep medicines safely; teach sleep hygiene.
Evaluation
Nursing care is successful if the patient can:
- Identify factors that interfere with normal sleep.
- Eliminate behaviours that disturb sleep.
- Use techniques that give a restful environment and promote sleep.
- Function effectively during waking hours.
- Say that he/she feels sleep was restful.
6. Pain
The word ‘pain’ comes from the Latin word ‘poena’, meaning a fine or a penalty. Pain is an unpleasant sensation that may vary from mild, localised discomfort to severe distress. It is the body’s protective mechanism – it warns of possible harm and makes us withdraw from the harmful situation. Pain is the main reason people seek health care. Pain also increases hospital stay, recovery time and gives poor patient outcome.
6.1 Pain Physiology
Nociceptors are sensory nerve endings that detect harmful (noxious) stimuli and send electrical signals to the nervous system. There are two main types:
| Fibre | Features | Type of pain |
|---|---|---|
| C-fibres | Non-myelinated, most common, slow conduction | Dull pain |
| A-delta fibres | Myelinated, fast conduction | Sharp, momentary pain |
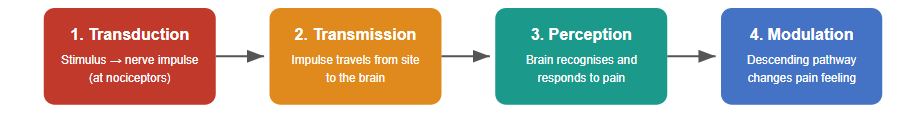
- Transduction: conversion of a mechanical, thermal or chemical stimulus into a nerve action potential at the free nerve endings (nociceptors).
- Transmission: movement of pain impulses from the site of transduction to the brain.
- Perception: the stage when pain is recognised, defined and responded to. There is no single place for pain perception; several brain structures are involved.
- Modulation: activation of the descending pain pathway. Depending on the type and degree of modulation, the nociceptive stimulus may or may not be felt as pain.
Memory trick:T-T-P-M – Transduction, Transmission, Perception, Modulation.
6.2 Types of Pain
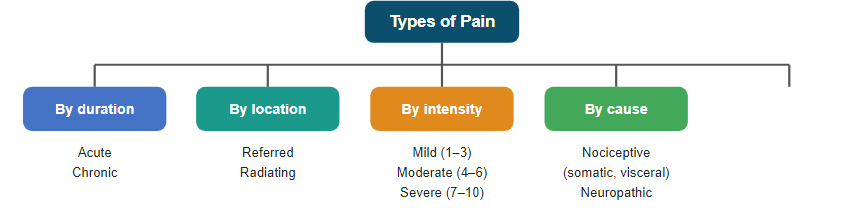
A. Based on duration
- Acute pain: complex, unpleasant, with an identifiable cause and defined pathology. It settles with healing of the tissue injury. It is a protective response to injury.
- Chronic pain: as per the American Pain Society (2007), pain persisting at least 3 months beyond the expected course of an acute injury or illness. The commonly accepted duration is more than 6 months or 1 month beyond the normal end of the condition causing the pain.
B. Based on location
- Referred pain: pain felt at a place other than the site of the stimulus. Example: cardiac pain felt in the shoulder or left arm, with or without chest pain.
- Radiating pain: pain that travels from one body part to another, starting at the injury site and spreading to a bigger area. Example: herniated disc pain travelling from the lower back to the leg.
C. Based on intensity

- Mild pain (1–3): nagging, annoying, but does not interfere with daily activities.
- Moderate pain (4–6): can be ignored for a short time but interferes significantly with daily activities.
- Severe pain (7–10): intense, excruciating, disabling; the person cannot do daily activities.
D. Based on cause
- Nociceptive pain: occurs when a healthy, working nervous system signals tissue damage. Example: burn pain makes you withdraw the hand. It can be somatic or visceral.
- Neuropathic pain: caused by damaged or malfunctioning nerves (injury, illness or unknown cause). Examples: diabetic peripheral neuropathy, phantom limb pain, spinal cord injury pain, trigeminal neuralgia. It may be peripheral or central.
6.3 Factors Affecting Pain
Pain is subjective – each person feels it differently. Factors: perception of pain, sociocultural factors, age, gender, meaning of pain, anxiety, past experiences and the placebo effect.
6.4 Pain Assessment
Pain is called the ‘fifth vital sign’ and should be assessed regularly and often.
A. History collection
- Pain characteristics, pattern of pain, area (location), intensity, quality
- Associated symptoms, history of pain relief measures, history of illness or injury
Additional point – PQRST / COLDSPA: Many teachers use PQRST to remember pain history – Provoking/palliating factors, Quality, Region/radiation, Severity, Timing.
B. Functional and psychosocial assessment
- Patient’s prior level of function; behaviour while doing functional tasks
- Effect of pain on ADL (work, self-care, exercise, leisure) – as told by patient and family
- Patient’s goal for pain management and level of function; impact on quality of life
- Cultural and developmental considerations
- Link of pain with depression, abuse, psychopathology, chemical or alcohol use
- Impact of pain on thinking ability (cognition)
C. Physiological assessment
Do a thorough physical assessment. Physiological signs alone cannot be used to measure pain.
- Tachycardia; change in respiratory rate/pattern; raised BP; fall in oxygen saturation
- Facial expression: grimacing, frowning, sad face
- Vocalisation: crying, moaning
- Body movements: guarding, resistance to moving
D. Common Pain Scales
| Scale | Description | Used for |
|---|---|---|
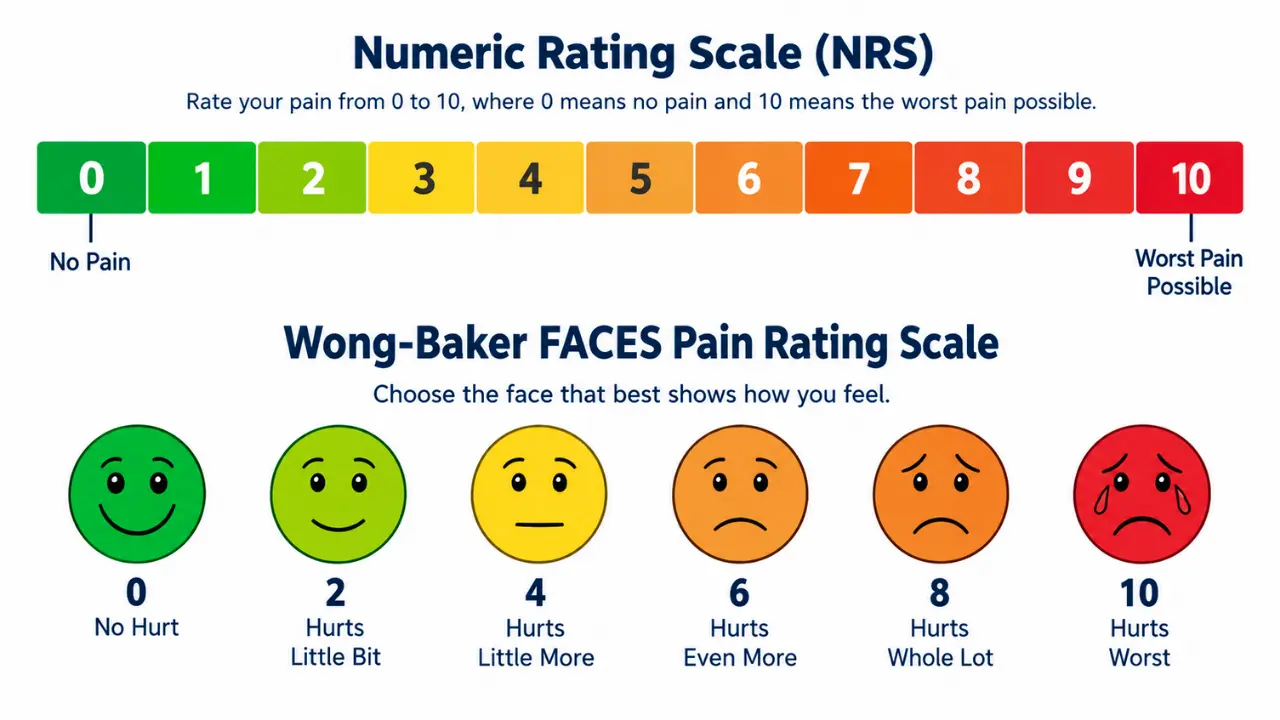
| Numeric rating scale | Rate pain from 0–10. | Most common in adults; patients aged 9 years and above who can use numbers. |
| Visual analogue scale (VAS) | A 10-cm line; one end ‘no pain’, other end ‘worst imaginable pain’. The person marks a spot on the line. | Adults who can understand the line. |
| Verbal pain intensity scale | Categorical scale using words such as mild, discomforting, distressing, horrible, excruciating. | Simple verbal rating. |
| Wong-Baker FACES scale | Drawn faces linked with numbers 0–10. | Children aged 3 years and older; also adults with developmental or communication problems. |
| FLACC scale | Face, Legs, Activity, Cry, Consolability – based on observed behaviour. | Mostly paediatric patients (infants/young children who cannot self-report). |
6.5 Pain Management
Basic principles of pain management
- Follow the principles of pain assessment.
- Every patient deserves adequate pain management.
- Base the treatment plan on the patient’s goals.
- Use both drug and non-drug (non-pharmacological) therapy.
- Follow a multidisciplinary approach.
- Evaluate the effectiveness of therapies.
- Prevent and/or manage medication side effects.
- Include patient and family teaching throughout assessment and treatment.
A. Pharmacological pain relief
WHO analgesic ladder (1986): A framework first developed to help doctors and nurses choose treatment for cancer pain.

Additional point: The ladder matches the pain intensity. Step 1: non-opioids (paracetamol, NSAIDs) for mild pain; Step 2: weak opioids (e.g., codeine, tramadol) with or without non-opioids for moderate pain; Step 3: strong opioids (e.g., morphine) for severe pain. Always check the drug order and your institution’s protocol.
| Drug group | Key points |
|---|---|
| Non-opioids (NSAIDs) | Primary drugs for acute and chronic pain from trauma, arthritis, surgery, cancer. Both analgesic and anti-inflammatory. Aspirin is effective for mild pain, but its use is limited by gastric upset, platelet dysfunction and bleeding. |
| Opioids | Most powerful analgesics, given for moderate to severe pain when non-opioids are not enough. Classified as mild and strong opioids. As per the textbook, examples of mild opioids: tramadol, codeine, oxycodone, hydrocodone. Side effects: respiratory depression (most serious, with IV, subcutaneous or epidural route), constipation, nausea and vomiting, sedation, dependence, tolerance. |
| Adjuvant (co-analgesic) drugs | Used along with opioid and non-opioid drugs. Originally made for other uses (e.g., antiseizure, antidepressants) and later found useful for pain. |
| Invasive therapies | Surgeries, injections or implanted devices: therapeutic nerve blocks, neuroablative techniques, neuroaugmentation, implantable opioid infusion pumps. |
B. Non-pharmacological pain relief
| Group | Methods |
|---|---|
| Physical | Massage; physical exercise; heat therapy; cold therapy |
| Electrical stimulation | TENS (Transcutaneous Electrical Nerve Stimulation); PENS (Percutaneous Electrical Nerve Stimulation) |
| Complementary / alternative | Acupuncture; acupressure; therapeutic touch; biofeedback; music therapy |
| Mind–body | Diversional therapy; hypnosis; relaxation strategies; cognitive behavioural therapy |
6.6 Nursing Management of a Patient with Pain
| Area | What the nurse does |
|---|---|
| 1. Alleviating anxiety | Stay with the patient; let the patient talk about feelings and fears; show empathy and willingness to listen; give a sense of control by involving the patient in the care plan; use therapeutic touch, back rub or a cool cloth to relax; tell the patient when a procedure is likely to be painful and encourage the patient to express pain. |
| 2. Distraction / diversion | Pain perception is reduced by reducing conscious awareness of pain. Works better with mild pain than severe pain. Examples: occupational therapy, conversation, reading, watching TV, listening to music, meditation. |
| 3. Combating anticipatory fears | Fear that occurs before the painful stimulus. Before painful procedures: explain what to expect (encourages relaxation and reduces muscle resistance, which itself causes pain); discuss the kind of pain expected; help the patient to take a body position that makes the procedure easier to tolerate. |
| 4. Providing physical care | Protect from local irritation or inflammation (infection, thrombosis, muscle spasm, strain); identify the source of pain and remove or reduce it; handle sensitive or injured tissue gently; do painful procedures when pain-relieving medicine is at its maximum effect. |
Chapter Focus Points (Quick Revision)
- Comfort is multidimensional – physical, psychospiritual, sociocultural and environmental.
- Positioning means placing the person in correct body alignment as needed therapeutically.
- Sleep is a complex rhythmic state of repeated cycles; it is crucial for physical, mental and emotional well-being.
- Pain is multidimensional, individual and subjective. It has four phases: transduction, transmission, perception and modulation.
One-Page Cheat Sheet (Numbers to Remember)
| Topic | Key number |
|---|---|
| Sleep needed for physical comfort | At least 6–8 hours |
| Change position of helpless patient | Every 2 hours |
| Fowler’s position | Head and trunk raised 15°–90° |
| Cardiac / orthopneic position | 90° |
| Trendelenburg | About 30° below horizontal |
| Hand roll | 2–3 inch diameter, 4–5 inch long |
| NREM / REM share of sleep | 75% / 20–25% |
| Stage I / II / III (NREM) share | 5% / 50–55% / 20% |
| REM begins after | 70–90 minutes |
| One sleep cycle; cycles per night | 90–100 min; 4–5 |
| Chronic insomnia | ≥ 3 times/week for ≥ 3 months |
| Narcolepsy with cataplexy | About 70% |
| Restless legs syndrome | About 15% of population |
| Chronotherapy | Delay sleep by 1–3 hours |
| Chronic pain | ≥ 3 months (commonly > 6 months) |
| Pain: mild / moderate / severe | 1–3 / 4–6 / 7–10 |
| Numeric scale / Wong-Baker age | 9+ years / 3+ years |
| VAS line length | 10 cm |
| WHO analgesic ladder | Developed in 1986 |
Multiple Choice Questions (MCQs)
- The word ‘comfort’ comes from the Latin word ‘comfortare’, which means:
a) Strengthen greatly b) Make quiet c) Give rest d) Remove pain - A Clinitron bed is used for:
a) Mild fever b) Advanced or multiple pressure ulcers and burns c) Normal delivery d) Dental procedures - Which device is used to prevent foot drop in an unconscious patient?
a) Bed cradle b) Hand roll c) Footboard d) Sandbag - A trochanter roll prevents:
a) Foot drop b) External rotation of the hip c) Contracture of fingers d) Heel sores - A wedge (abductor) pillow is used after:
a) Appendectomy b) Total hip replacement c) Tonsillectomy d) Cataract surgery - Bed blocks are used for which position?
a) Fowler’s b) Sims’ c) Trendelenburg d) Lithotomy - The main purpose of a cardiac bed is to:
a) Prevent infection b) Relieve dyspnoea c) Watch the stump d) Immobilise a fracture - In an amputation bed, the top linen is:
a) Divided into two parts b) Removed completely c) Folded under the patient d) Replaced by a cradle only - Which is the only bed position that allows full extension of hip and knee joints?
a) Supine b) Prone c) Lateral d) Fowler’s - In Fowler’s position the head and trunk are raised to:
a) 0°–15° b) 15°–90° c) 90°–180° d) 30° below horizontal - Which position is used for rectal examination?
a) Sims’ b) Prone c) Supine d) Fowler’s - A helpless patient’s position should be changed every:
a) 30 minutes b) 1 hour c) 2 hours d) 6 hours - NREM sleep forms about ______ of total sleep time.
a) 25% b) 50% c) 75% d) 100% - REM sleep starts after about:
a) 5–10 minutes b) 70–90 minutes c) 3 hours d) 5 hours - One sleep cycle lasts about:
a) 30–40 minutes b) 60 minutes c) 90–100 minutes d) 180 minutes - The deepest stage of sleep is:
a) NREM stage I b) NREM stage II c) NREM stage III d) Wakefulness - Chronic insomnia is insomnia occurring:
a) Once a month for 1 week b) At least 3 times a week for at least 3 months c) For 1 day d) For 2 weeks - The definitive treatment for moderate and severe obstructive sleep apnoea is:
a) Mandibular advancement device b) CPAP c) Stimulant drugs d) Light therapy - Cataplexy is associated with:
a) Narcolepsy b) Insomnia c) Restless legs syndrome d) Jet lag - Sleepwalking is known as:
a) Somnambulism b) Enuresis c) Nightmare disorder d) Sleep terror - Which nerve fibres carry sharp and momentary pain quickly?
a) C-fibres b) A-delta fibres c) Both equally d) None - Conversion of a stimulus into a nerve action potential is called:
a) Transduction b) Modulation c) Perception d) Transmission - The Wong-Baker FACES scale is appropriate for patients aged:
a) 3 years and above b) 9 years and above only c) Adults only d) Newborns only - FLACC stands for:
a) Face, Legs, Activity, Cry, Consolability b) Fever, Legs, Anxiety, Cry, Comfort c) Face, Limbs, Activity, Cough, Calm d) Fear, Legs, Action, Cry, Care - Pain is often called the:
a) First vital sign b) Fifth vital sign c) Last vital sign d) Third vital sign
Answer Key:
1-a, 2-b, 3-c, 4-b, 5-b, 6-c, 7-b, 8-a, 9-b, 10-b, 11-a, 12-c, 13-c, 14-b, 15-c, 16-c, 17-b, 18-b, 19-a, 20-a, 21-b, 22-a, 23-a, 24-a, 25-b
Comfort, Rest, Sleep and Pain Important Questions (INC / University Exam Pattern)
These are the types of questions that are commonly asked from this chapter in nursing university exams under the INC syllabus. Questions are grouped by marks.
Long Answer Questions (10 / 15 marks)
- Define comfort. Explain the factors influencing comfort. Describe any ten comfort devices used in hospital with their uses.
- Define bed making. Describe the purposes and principles of bed making. Explain the types of beds with their purposes.
- Define positioning. Explain the principles and purposes of positioning. Describe the various therapeutic positions with their uses.
- Describe the stages of sleep and sleep cycle. Explain the factors affecting sleep and the common sleep disorders.
- Define sleep disorders. Describe insomnia and obstructive sleep apnoea with their management. Write the nursing process for a patient with sleep disturbance.
- Define pain. Explain the physiology and types of pain. Describe pain assessment and the scales used.
- Discuss pharmacological and non-pharmacological pain management. Explain the nursing management of a patient with pain.
Short Answer Questions (5 marks)
- Purposes of comfort devices.
- Special beds (Gatch, electric, Clinitron).
- Trochanter roll, hand roll and footboard – uses.
- Principles of bed making.
- Body mechanics during bed making.
- Occupied bed – purposes.
- Cardiac bed / fracture bed / burn bed / amputation bed – purposes.
- Principles of positioning.
- Fowler’s position and its uses.
- Sims’ position / lithotomy position / knee-chest position.
- Trendelenburg and reverse Trendelenburg positions.
- REM sleep and NREM sleep – differences.
- Insomnia – types, risk factors and management.
- Narcolepsy.
- Shift work disorder and jet lag.
- Parasomnias.
- Sleep deprivation.
- Pain pathway / process of pain mechanism.
- Types of pain based on duration, location and intensity.
- Pain scales.
- WHO analgesic ladder.
- Non-pharmacological methods of pain relief.
- Nursing measures to reduce anxiety in a patient with pain.
Very Short Answer Questions (2 marks)
- Define comfort.
- Name four types of comfort.
- What is a bed cradle?
- Define bed making.
- What is an unoccupied bed?
- Define positioning.
- Define sleep and rest.
- What is polysomnography?
- What is a hypnogram?
- How long does one sleep cycle last?
- Define insomnia.
- What is cataplexy?
- Name two circadian rhythm sleep–wake disorders.
- Define pain.
- What are nociceptors?
- Differentiate referred pain and radiating pain.
- What does FLACC stand for?
- Name two adverse effects of opioids.
- Name any four non-pharmacological pain relief methods.
Hints for Writing Answers
- Start with a definition, then give types/classification, then explain each point with its purpose or use.
- Draw neat diagrams: hypnogram (sleep cycle), phases of pain, WHO analgesic ladder, positions. Diagrams carry extra marks.
- Write numbers correctly (15°–90°, 90–100 min, 70–90 min, 0–10, 1–3 / 4–6 / 7–10).
- In nursing process answers, follow the order: Assessment – Diagnosis – Planning/Intervention – Evaluation.
- Underline key words and use headings.
Reference: Textbook of Nursing Foundation for BSc Nursing Students (as per the revised INC syllabus), Jyoti Kathwal, Vision Health Sciences Publisher.
Disclaimer: These notes are for educational purposes. Drug use and hospital procedures may vary between institutions; always follow your hospital policy, doctor’s orders and your teacher’s instructions.
- Also read:
- CHAPTER 1: Introduction to Health and Illness, Nursing Foundation Unit 1 Notes PDF
- CHAPTER 2: Health Care Delivery System, Nursing Foundation Unit 2 BSc Nursing Notes
- Chapter 3: Nursing as a Profession and History of Nursing in India: BSc Nursing 1st Semester Notes (Nursing Foundation)
- CHAPTER 4: Hospital Admission and Discharge: Complete BSc Nursing Notes | 1st Semester Notes (Nursing Foundation)
- CHAPTER 5: Communication and Nurse Patient Relationship: Complete Notes | BSc Nursing 1st Semester Notes (Nursing Foundation)
- Chapter 6: Patient Education in Nursing: Notes for BSc Nursing 1st Semester, Nursing Foundation Notes with MCQs & Important Questions
- Chapter 7: The Nursing Process: Complete Notes for BSc Nursing, 1st Semester, Nursing Foundation
- Chapter 8: Documentation and Reporting: Notes with MCQs and Important Questions for BSc Nursing 1st Year, Nursing Foundation Notes
- Vital Signs: Assessment & Regulation Complete Notes for Nursing With MCQ and Important Questions
- Machinery, Equipment and Linen in Hospital: Types, Care, Cleaning, Indent and Inventory
- Infection Control in Clinical Settings: Guidelines, Methods, Hand Hygiene, PPE and Safety Measures Complete Nursing Notes






